Persistent knee pain, swelling, stiffness and declining walking ability can make ordinary tasks feel increasingly limited, but those symptoms do not automatically mean you need an operation. By the end, you will understand how surgeons assess the source of pain, distinguish total from partial replacement, weigh non-surgical care, and prepare for realistic recovery and long-term results.
Key takeaways
- Cartilage damage across one or more knee compartments guides replacement type.
- Persistent pain and limited function warrant an orthopaedic assessment.
- Compare non-surgical care with replacement based on symptoms and daily limitations.
- Recovery restores movement gradually and still requires structured rehabilitation.
How Knee Damage Determines the Type of Replacement
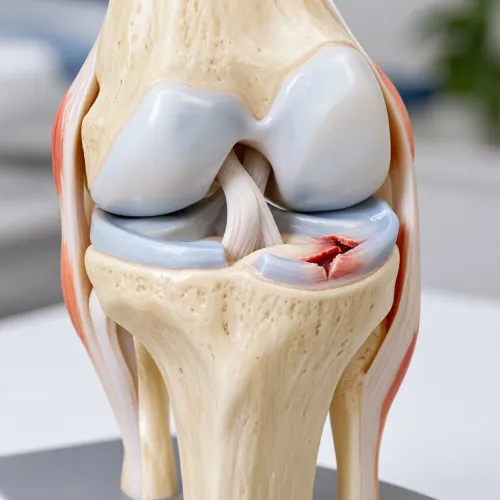
The extent of cartilage damage, rather than age alone, usually determines the knee replacement choice. The three compartments of the knee are the medial compartment on the inner side, the lateral compartment on the outer side and the patellofemoral compartment behind the kneecap.
| Option | Damage pattern | Usual implication |
|---|---|---|
| Total knee replacement | Arthritis affects two or all three compartments, or causes major deformity | Replaces the damaged joint surfaces across the femur and tibia, and may resurface the kneecap |
| Partial knee replacement | Disease is limited to one compartment, most commonly the medial compartment | Preserves the healthy compartments and more of the original knee |
| Partial lateral or patellofemoral replacement | Damage is confined to the lateral compartment or patellofemoral compartment | Suitable only when the remaining cartilage and alignment are sound |
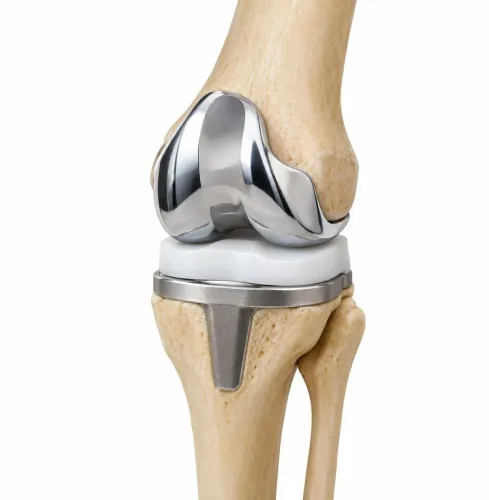
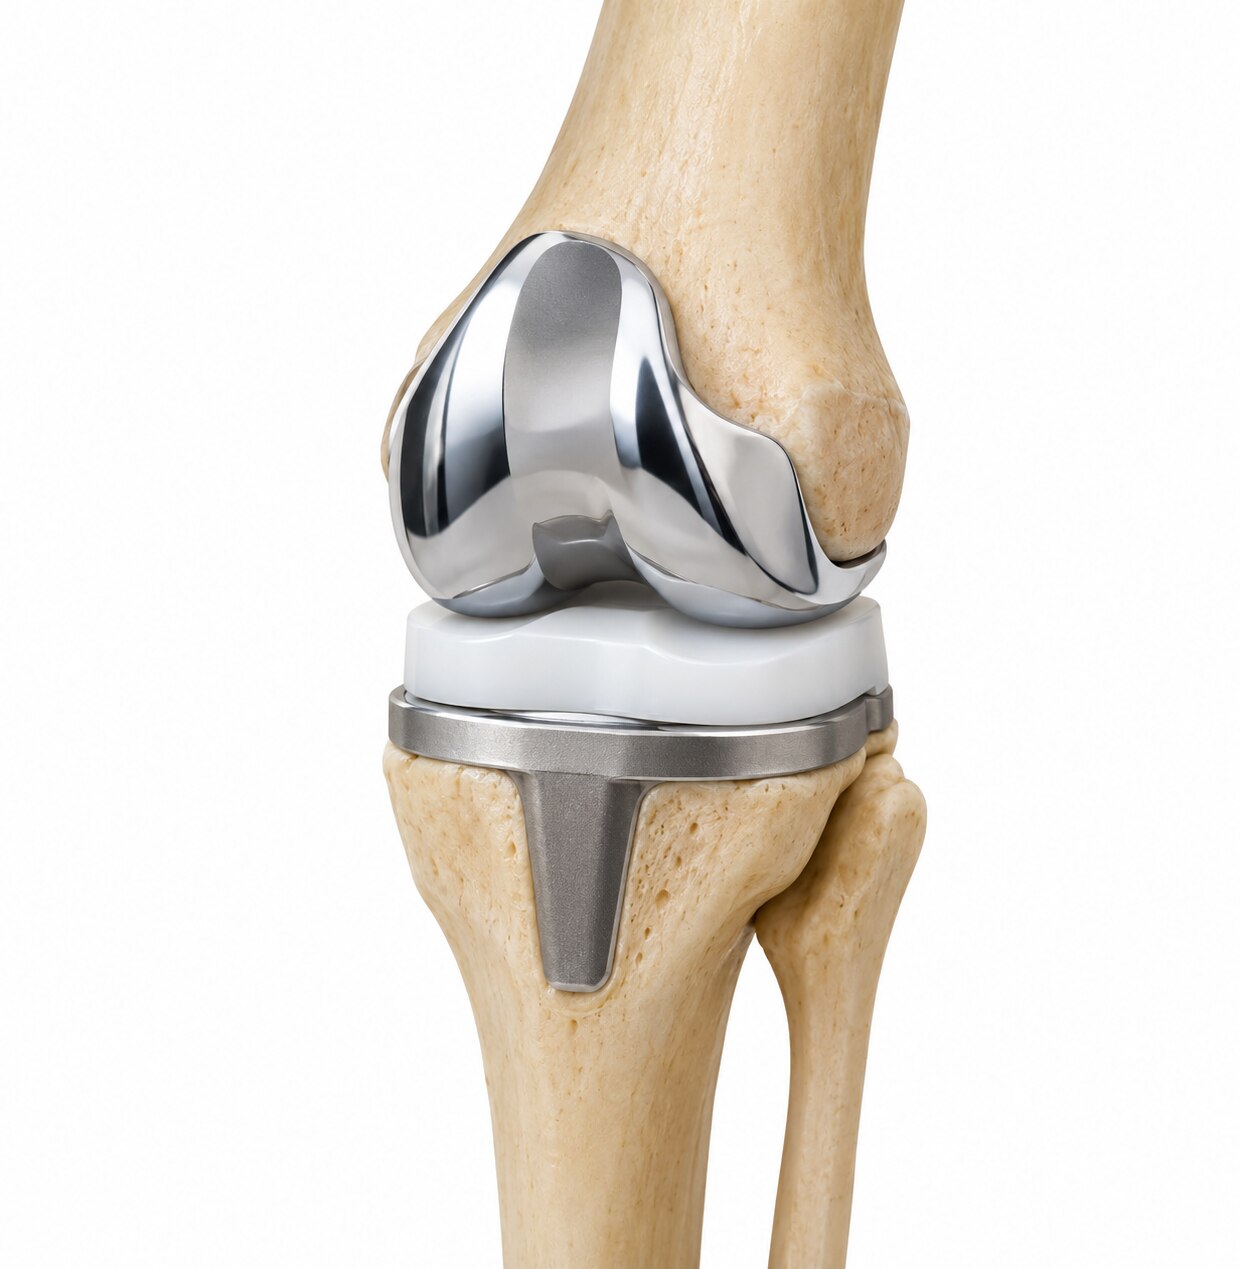
The key knee replacement choice differences between total and partial knee replacement include how much joint surface is removed and how much natural knee structure remains. A total replacement does not replace the entire knee: the surgeon removes damaged cartilage and a small amount of bone, then inserts metal components with a plastic spacer.
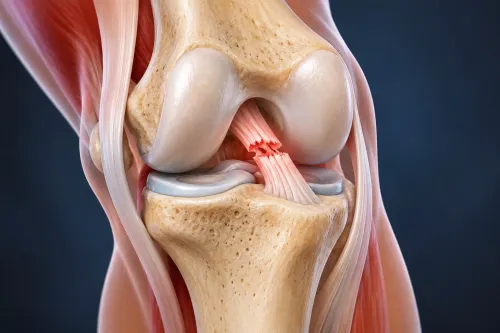
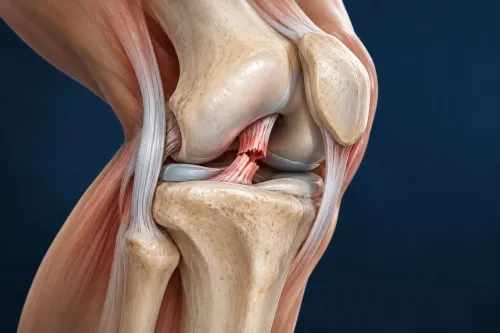
A partial replacement requires a stable, well-functioning ligament condition, especially an intact anterior cruciate ligament, plus correctable alignment and no substantial arthritis elsewhere. Widespread arthritis, inflammatory disease, fixed deformity or significant ligament damage points toward total replacement.
Weight-bearing X-rays and a physical examination confirm whether the damage is truly isolated; MRI helps when the diagnosis or ligament condition remains unclear.
When Symptoms Justify an Assessment and How Candidacy Is Tested
An assessment is justified when knee symptoms limit daily life and persist despite appropriate non-surgical treatment—not because you reached a certain age or because an X-ray looks severe. The decision combines pain, lost function, physical examination findings and radiographic joint damage.
- Persistent knee pain at rest or night pain that disrupts sleep
- Knee swelling and stiffness that restrict bending, straightening or getting up from a chair
- Deformity, difficulty climbing stairs, or a reduced walking distance
- Pain that continues after physiotherapy, weight reduction, medicines, injections, braces or activity changes
- Increasing reliance on a stick, support from furniture or help with routine activities
Your medical history identifies previous injuries or operations, inflammatory arthritis, infections, blood-clot risk, diabetes, heart or lung disease, medicines and other factors that affect surgery. During the physical examination, the clinician watches you walk and checks tenderness, range of motion, muscle strength, ligament stability, swelling and standing alignment.
A fixed deformity, severe movement restriction or unstable ligament changes the treatment discussion.
Imaging confirms whether symptoms match structural damage. Standing alignment X-rays and weight-bearing knee radiographs show joint-space loss, bone changes and how the leg loads the knee. MRI is useful when the diagnosis or ligament condition remains unclear, but it is not a substitute for symptoms and examination.
A worn-looking X-ray without disabling pain does not establish candidacy; severe symptoms with matching findings do.
Choosing Between Non-Surgical Care and Joint Replacement
Continue non-surgical care when arthritis pain remains manageable and you can still walk, sleep and work with acceptable limits. Physiotherapy for knee arthritis builds strength and preserves movement; weight reduction lowers joint loading; pain medicines, knee injections, braces and activity modification can control symptoms while you remain functional.
| Option | When it fits | What to watch |
|---|---|---|
| Physiotherapy and activity modification | Strength is poor, movement is limited, but function remains usable | Progress should be measured by walking distance, stairs and sleep, not pain alone |
| Weight reduction | Excess body weight increases load and surgical risk | It supports treatment but cannot restore severely damaged cartilage |
| Pain medicines or knee injections | Flares interrupt activity despite exercise changes | Side effects, temporary benefit or repeated injections can limit usefulness |
| Braces | Alignment-related pain improves with support | A brace that causes numbness or does not improve walking is not helping |
| Joint replacement assessment | Persistent pain and loss of function continue despite a properly tried programme | Surgery brings substantial improvement, but persistent pain remains possible |
Replacement is not the first choice for hip or spine pain that only feels like knee pain, an infection, or an isolated meniscal problem without advanced arthritis. Treating those conditions first avoids replacing a knee that is not causing the disability.
Seek reassessment when pain persists at rest or at night, walking distance keeps shrinking, stairs become difficult, or treatment no longer preserves daily function. A decision should combine symptoms, examination and weight-bearing X-rays—not an X-ray alone or a particular age.
What the Implant Can Restore—and What Recovery Still Requires
A knee replacement removes damaged cartilage and a small amount of bone, then rebuilds the joint with a femoral metal component, tibial metal tray and polyethylene plastic insert. A patellar resurfacing component may cover the underside of the kneecap; ligament treatment depends on the implant design and your knee.
The aim is less pain, better walking, easier stairs and improved daily function—not a normal, original knee. Compare what improves with what still requires effort:
| Restored or improved | What still requires planning |
|---|---|
| Painful bone-on-bone movement | Rehabilitation for knee extension, quadriceps strength and walking |
| Walking distance and stair use | Stiffness, swelling and altered sensation |
| Joint alignment and stability | Kneeling may remain uncomfortable or difficult |
| Daily mobility | High-impact activity can aggravate symptoms |
Rehabilitation continues after the incision heals. Your programme may include home exercises or supervised therapy; forcing a stiff knee or skipping exercises can limit knee extension and encourage persistent pain.
Implant durability is strong but not lifetime-guaranteed: registry and case-series data estimate about 93% remain in place at 15 years, 90% at 20 years and 82% at 25 years. Infection, loosening, wear, instability, fracture around the implant, stiffness and persistent pain can require revision surgery, which may involve removing well-fixed parts and managing bone loss.
Deep infection is uncommon but serious, reported at about 1–2%. Fever, wound drainage, increasing redness or worsening pain after initial improvement needs urgent assessment.
How Surgeons Compare Total, Partial and Robotic-Assisted Replacement
The final choice should match the pattern of damage, ligament condition and your ability to recover safely—not the newest equipment. Total knee replacement versus partial knee replacement is mainly an operation and implant-design decision; robotic assistance is a planning and execution aid.
| Option | Operation and implant design | What to compare |
|---|---|---|
| Total knee replacement | Resurfaces the damaged femur and tibia, with possible kneecap resurfacing; implant design determines ligament treatment and movement | Damage in multiple compartments, deformity and ligament stability |
| Partial knee replacement | Replaces one compartment while preserving healthy bone, cartilage and functioning ligaments | Disease confined to one compartment, correctable alignment and reliable patient selection |
| Robotic-assisted knee replacement | Uses imaging, computer navigation and instruments to guide component positioning | Whether the planning improves accuracy in your anatomy; it does not replace implant selection or soft-tissue balancing |
Ask how the chosen implant suits your activity, bone quality and ligament status, rather than assuming robotic-assisted knee replacement guarantees less pain or longer survival. Better alignment has not consistently produced better short- or medium-term outcomes.
Before surgery, address smoking cessation, and discuss whether a BMI above 40 raises wound, infection or anaesthetic risks. Blood-clot prevention, early mobilisation, pain control and physiotherapy matter more to recovery than the presence of a robot. Same-day discharge requires safe walking, stable observations, controlled nausea and pain, and dependable home support.
Dr Ronak Kothari can help structure that comparison around your examination and imaging.
Related services
Knee Replacement Surgery Knee replacement surgery, or knee arthroplasty, is a procedure to replace a damaged knee joint with an artificial implant made of metal and plastic. View service → |
Robotic Joint Replacement Dr. Ronak Kothari, a leading Orthopaedic Surgeon, specializes in Robotic Joint Replacement Surgery, offering state-of-the-art precision and enhanced... View service → |
Frequently asked questions
How does knee damage determine the type of replacement?
Damage limited to one knee compartment can support a partial replacement, while damage across multiple compartments may require total replacement.
When should you seek an assessment for knee replacement?
Seek an assessment when knee pain, stiffness or limited movement continues to restrict walking, work, sleep or everyday activities.
How do surgeons test whether you are a candidate for knee replacement?
The assessment combines your symptoms and activity limitations with a physical examination and imaging of the damaged knee.
When should you choose non-surgical care instead of knee replacement?
Choose non-surgical care when symptoms remain manageable and treatment can preserve function without the risks and rehabilitation required after surgery.
What can knee replacement restore, and what does recovery require?
Replacement can reduce pain and improve mobility, but recovery still requires rehabilitation, progressive exercises and time to regain strength and movement.
Related service
Partial Knee Replacement Dr. Ronak Kothari, a proficient Orthopaedic Surgeon, offers advanced Partial Knee Replacement (Unicompartmental Knee Replacement) procedures designed... View service → |